On this page
- What knee osteoarthritis is
- What standard treatment looks like first
- Why MSCs are studied for this joint
- What the trials actually found
- What those findings do not establish
- Structural change versus feeling better
- Who tends to be considered
- Risks worth weighing
- The alternatives, stated fairly
- Reading further
- Frequently asked questions
- Requesting a medical evaluation
If there is one place where regenerative medicine has genuine human evidence behind it, this is it. Knee osteoarthritis and stem cell therapy has been studied in randomised controlled trials and pooled in more than one meta-analysis — which still does not make it a settled treatment, and the gap between those two statements is what this page is about.
What knee osteoarthritis is
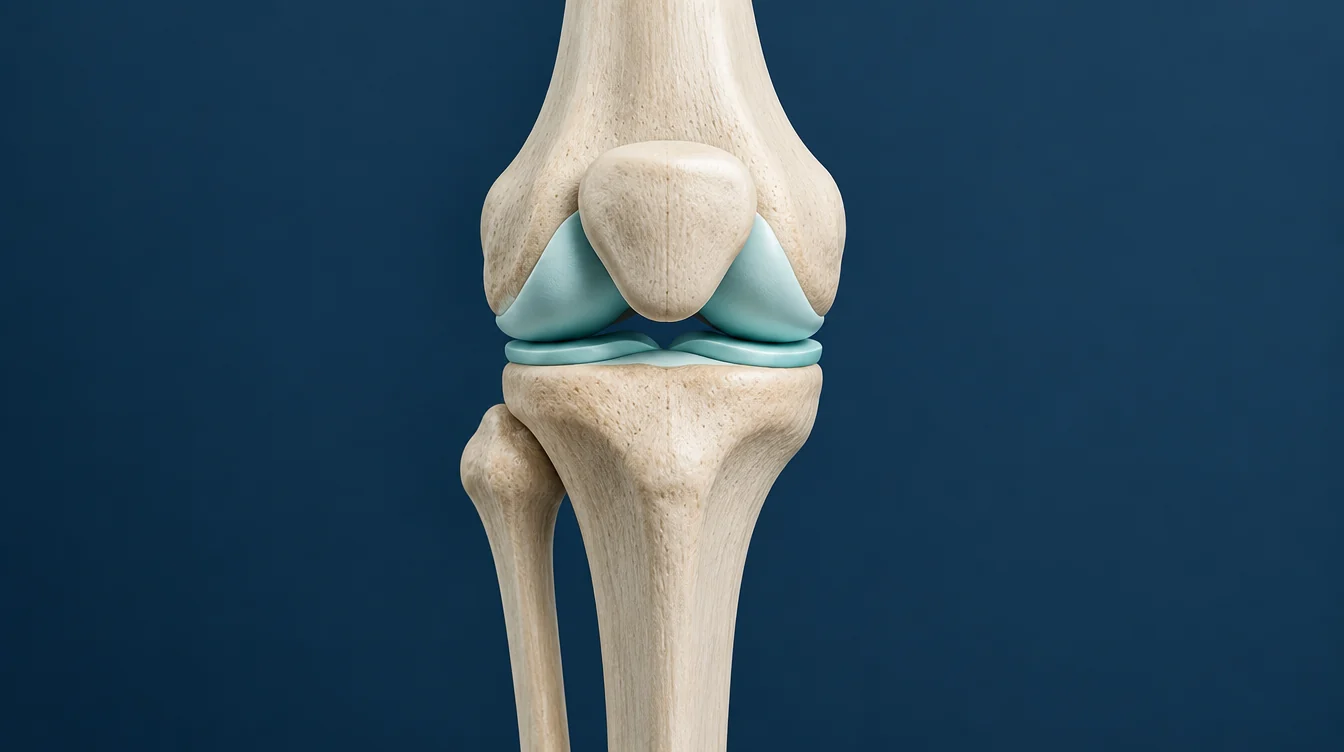
Articular cartilage covers the ends of the bones inside the knee and lets them move against each other with very little friction. In osteoarthritis that surface thins and roughens, the underlying bone changes, and the joint lining becomes inflamed.
The result is pain that is worse with use, stiffness after rest, and a joint that gradually does less. It is mechanical, inflammatory and progressive, and it is extremely common after middle age.
It is worth knowing that X-ray appearance and symptoms correspond poorly. Knees that look severe on film can hurt little; knees that look mild can hurt a great deal.
What standard treatment looks like first
This comes before any discussion of cell therapy, and any clinic that skips it is skipping the part with the best evidence.
Weight management where relevant, and structured exercise — particularly quadriceps strengthening — have solid evidence and are consistently underused. Simple analgesia and topical anti-inflammatories help many people. Corticosteroid injection gives short-term relief.
At the far end, knee replacement is one of the more reliably effective operations in medicine. Regenerative treatment is generally discussed by people who are past the first group of options and not yet ready for the last.
Why MSCs are studied for this joint
Two proposed mechanisms appear in the literature: that the cells modulate the inflammatory environment inside the joint, and that they influence the behaviour of resident cells rather than turning into cartilage themselves.
The older idea — that injected cells become new cartilage — has largely not survived contact with the evidence. What the trials mostly measure is symptom change, not new tissue.
Mechanism is a reason to run a trial. It is not a result. See MSC immunomodulation.
What the trials actually found
A 2025 systematic review and meta-analysis pooled randomised controlled trials of MSCs in knee osteoarthritis — Efficacy and safety of mesenchymal stem cells in knee osteoarthritis.
A phase III randomised trial of autologous adipose-derived MSCs injected into the joint reported on both efficacy and safety — Clinical Efficacy and Safety of the Intra-articular Injection of Autologous Adipose-Derived Mesenchymal Stem Cells.
An earlier randomised trial of umbilical cord-derived MSCs found that repeated dosing outperformed a single dose — Umbilical Cord-Derived Mesenchymal Stromal Cells for Knee Osteoarthritis — which matters because it suggests one injection may not be the right comparison to make.
A further randomised trial injected autologous adipose tissue-derived cells into the joint — Intra-Articular Injection of Autologous Adipose Tissue-Derived Mesenchymal Stem Cells — and a 2025 prospective randomised study looked specifically at whether cartilage changes in early disease — Cartilage Regeneration Potential in Early Osteoarthritis of the Knee.
What those findings do not establish
Most of these trials are small. Blinding is difficult when one arm involves a harvest procedure. Follow-up is commonly six to twenty-four months, which is short against a condition measured in decades.
Pain and function scores are subjective, and placebo response in knee injection trials is well recognised and substantial. A trial that shows improvement over baseline is a much weaker result than one showing improvement over a sham injection.
Cell source, dose and preparation differ so much between studies that pooling them involves real assumptions — which the network meta-analysis exists to address — which cell and type are more beneficial.
Structural change versus feeling better
These are different endpoints and they are often conflated in marketing.
Symptom improvement means less pain and better function on a questionnaire. Structural change means a measurable difference in cartilage on imaging. The first is what most trials report; the second is far less consistently demonstrated.
Being told a joint has been rebuilt is a much larger claim than being told pain scores fell — see cartilage regeneration research.
Who tends to be considered
Across the trial literature, participants generally had mild to moderate disease rather than end-stage, still had some cartilage remaining, and had already tried conservative management.
Severe bone-on-bone change, significant malalignment and inflammatory arthritis of a different type are common exclusions. So are active infection and malignancy.
Whether any of that describes you is a question for someone holding your imaging, not for a web page.
Risks worth weighing
The injection itself carries a small risk of joint infection, and a larger likelihood of transient pain and swelling for a few days afterwards.
Where cells are autologous, the harvest is a second procedure with its own risks at the donor site.
And there is the cost of an intervention that may do nothing for you, in a condition where the alternative options have better evidence — see adverse events.
The alternatives, stated fairly
Exercise therapy has evidence at least as good as anything discussed here, costs almost nothing, and is the option most often skipped.
Corticosteroid and hyaluronic acid injections both have their own literature. PRP is cheaper, more widely available, and frequently confused with cell therapy.
Knee replacement remains the most reliable option for advanced disease, and deferring it has a cost of its own if the joint deteriorates meanwhile.
Reading further
The knee osteoarthritis studies page sets out each trial with its design, population, follow-up and limitations.
MSC therapy covers the cells themselves; osteoarthritis covers the condition across other joints.
The cost page explains why quotes vary so widely for what sounds like the same treatment.
Two other knee problems are frequently treated as though this evidence covered them, and it does not — meniscus tears and ligament injuries each have their own much thinner literature.
Frequently asked questions
Does this rebuild cartilage?
Most trials measured pain and function, not cartilage thickness. Structural change is much less consistently shown than symptom change, and the two get conflated often.
How good is the evidence really?
Better than for any other indication discussed on this site — several randomised trials and more than one meta-analysis. Still limited by small samples, difficult blinding and short follow-up.
How long does any benefit last?
Trial follow-up is commonly six to twenty-four months. Beyond that the honest answer is that nobody has good data.
One injection or several?
A randomised trial of cord-derived cells found repeated dosing did better than a single dose, so the number of treatments is a fair question to ask any clinic.
Is it better than a steroid injection?
Head-to-head comparisons are limited. Steroid works quickly and briefly; the case made for cells is a longer effect, which the trials test imperfectly.
Will it mean I do not need a knee replacement?
No trial has shown that. Deferring replacement has its own cost if the joint continues to deteriorate, and that trade-off is worth discussing with an orthopaedic surgeon.
Does it work for bone-on-bone arthritis?
Severe end-stage disease was generally excluded from the trials, so evidence there is weakest exactly where people most want it to be strong.
What should I try first?
Structured exercise and quadriceps strengthening, which have evidence as good as anything here and are consistently underused.
Requesting a medical evaluation
Nothing on this page establishes whether any treatment is appropriate for you. That needs your history, your imaging and your current medications read by a clinician. If you would like that review, send your records and we will tell you honestly whether there is anything worth discussing — including when the answer is no.
This page is general information, not medical advice, and does not create a doctor–patient relationship. Regenerative treatments discussed here are in most cases investigational. Discuss any treatment with a clinician who knows your history.